Function(s):
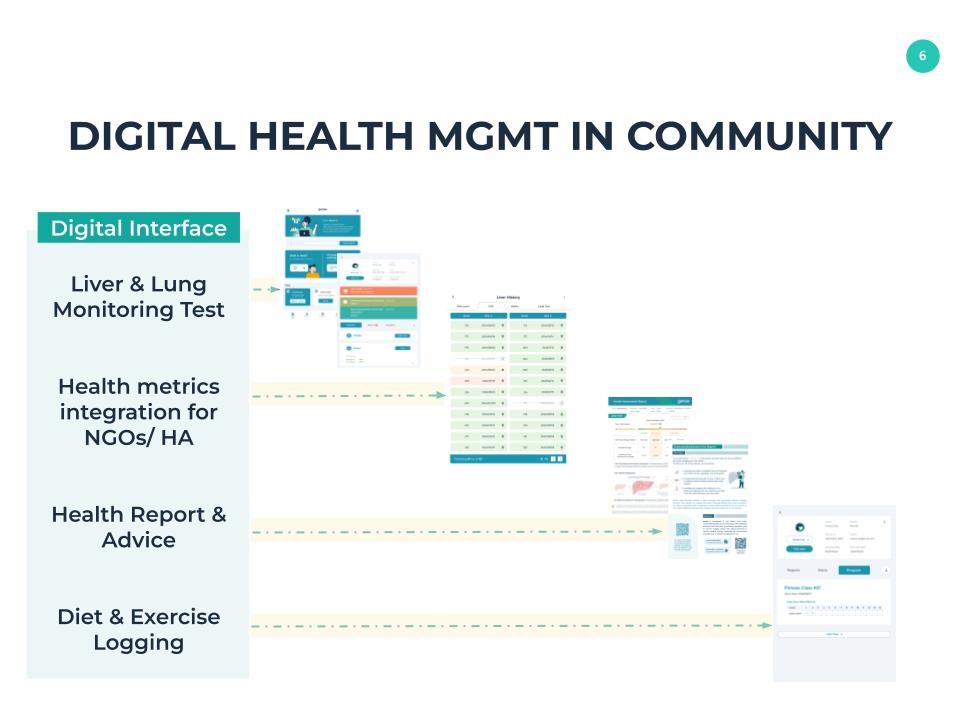
This is a digital medical-social product for community-based chronic disease management, designed to support low-income and elderly residents living with COPD and fatty liver disease. It connects hospitals, NGOs, community workers, and service users through one integrated platform that coordinates care, monitors health risks, and enables continuous follow-up beyond hospital discharge.
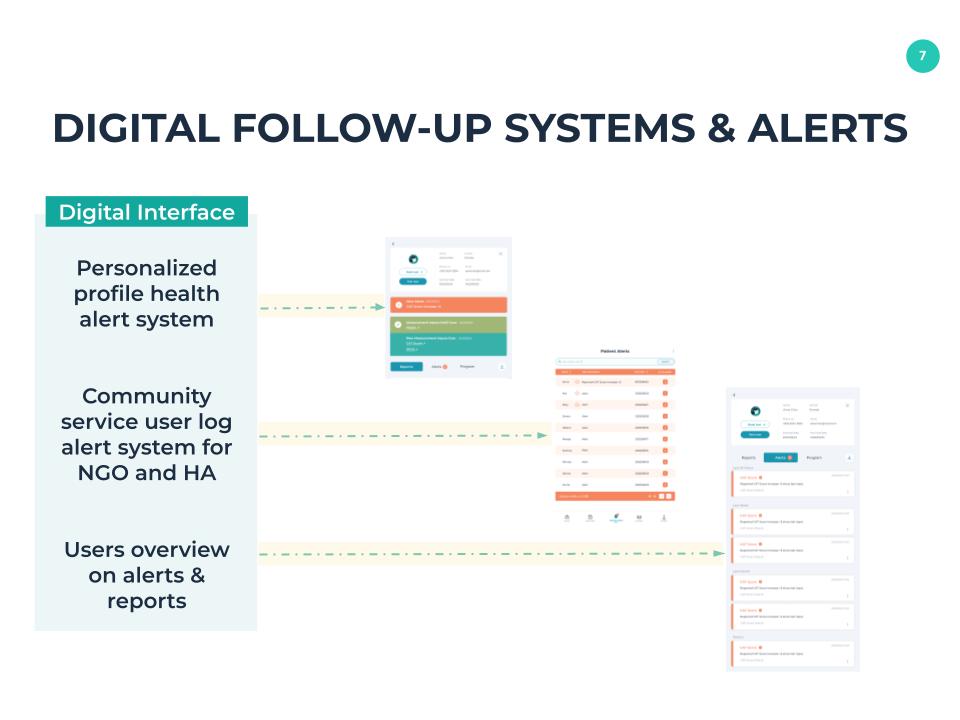
The system provides digital care pathways, risk alerts, self-tracking tools, and progress dashboards for users, carers, and community personnel. It supports structured post-discharge follow-up, lifestyle coaching, and regular monitoring of symptoms, lung function, weight, blood pressure, and other key indicators. Community workers can access standardized protocols, training materials, and real-time data to guide interventions, while healthcare professionals can review alerts and high-risk cases remotely.
By embedding clinical expertise into a community delivery model, the platform extends hospital capacity into everyday life. It reduces fragmented care, prevents avoidable complications and readmissions, and empowers users to manage their conditions with confidence. The social mission is to close the gap between hospital and community, improve health equity for underprivileged groups, and create a sustainable, scalable model for chronic disease management in Hong Kong.